








लिवर कैंसर के लक्षण (Liver Cancer Symptoms) सबसे अधिक खोजे जाने वाले स्वास्थ्य विषयों में से एक हैं, और साथ ही सबसे भ्रामक भी — क्योंकि यह बीमारी शुरुआती अवस्था में असामान्य रूप से चुप रहती है। लिवर के अंदर दर्द महसूस कराने वाली कोई तंत्रिका (Pain Fiber) नहीं होती, इसमें काम करने की बड़ी अतिरिक्त क्षमता होती है, और एक ट्यूमर (Tumor) लंबे समय तक बढ़ता रह सकता है — बिना कुछ महसूस हुए। इसीलिए यह सवाल कि किन संकेतों पर ध्यान देना चाहिए, इसका सच्चा जवाब एक अलग सवाल से शुरू होता है: क्या आप उस समूह में हैं जिनकी नियमित जांच (Screening) होनी चाहिए, बजाय किसी लक्षण का इंतज़ार करने के। नेशनल कैंसर इंस्टीट्यूट (National Cancer Institute) के अनुसार, 2026 में अमेरिका में लिवर और इंट्राहेपेटिक बाइल डक्ट (Intrahepatic Bile Duct) के लगभग 42,340 नए मामले सामने आने की उम्मीद है, और सभी अवस्थाओं को मिलाकर पाँच साल की सापेक्ष जीवित रहने की दर (Five-Year Relative Survival Rate) 21.9 प्रतिशत है — जो इस बात पर बहुत निर्भर करती है कि बीमारी कितनी जल्दी पकड़ी गई। यह गाइड बताती है कि लक्षण वास्तव में क्या होते हैं, वे कब प्रकट होते हैं, किसे खतरा अधिक है, और इस जानकारी के साथ क्या करना चाहिए।.
लिवर कैंसर के लक्षण इतनी देर से क्यों दिखते हैं
लिवर की तीन विशेषताएँ इस देरी को समझाती हैं। इसमें बहुत अधिक अतिरिक्त क्षमता होती है, इसलिए इसका एक बड़ा हिस्सा प्रभावित होने के बाद भी रक्त परीक्षण (Blood Tests) या रोज़मर्रा की कार्यप्रणाली में कोई बदलाव नहीं आता। इसके आंतरिक ऊतक (Internal Tissue) में संवेदी तंत्रिकाएँ (Sensory Nerves) नहीं होतीं, इसलिए अंग के भीतर बढ़ता ट्यूमर तब तक दर्द नहीं देता जब तक वह इसके चारों ओर की झिल्ली (Capsule) को न खींचे या किसी पड़ोसी अंग पर दबाव न डाले। और अधिकांश लिवर कैंसर पुरानी लिवर बीमारी (Chronic Liver Disease) के ऊपर विकसित होता है — इसलिए जो थकान, भूख न लगना और पेट में बेचैनी अंततः महसूस होती है, उसे अक्सर पहले से मौजूद सिरोसिस (Cirrhosis) या हेपेटाइटिस (Hepatitis) का असर मान लिया जाता है।.
हेपेटोसेलुलर कार्सिनोमा (Hepatocellular Carcinoma) प्राथमिक लिवर कैंसर (Primary Liver Cancer) के लगभग 90 प्रतिशत मामलों के लिए ज़िम्मेदार है। इंट्राहेपेटिक बाइल डक्ट कैंसर (Intrahepatic Bile Duct Cancer) शेष मामलों का अधिकांश हिस्सा बनाता है — लगभग 10 से 20 प्रतिशत — और हेपेटिक एंजियोसार्कोमा (Hepatic Angiosarcoma) बहुत दुर्लभ है, लगभग 1 प्रतिशत। प्राथमिक लिवर कैंसर, जो लिवर में ही शुरू होता है, उस कैंसर से अलग बीमारी है जो किसी अन्य अंग से लिवर में फैलता है — और ये दोनों एक-दूसरे के स्थान पर नहीं रखे जा सकते, भले ही बातचीत में दोनों को "लिवर कैंसर" कहा जाए।.
लिवर कैंसर के शुरुआती लक्षण
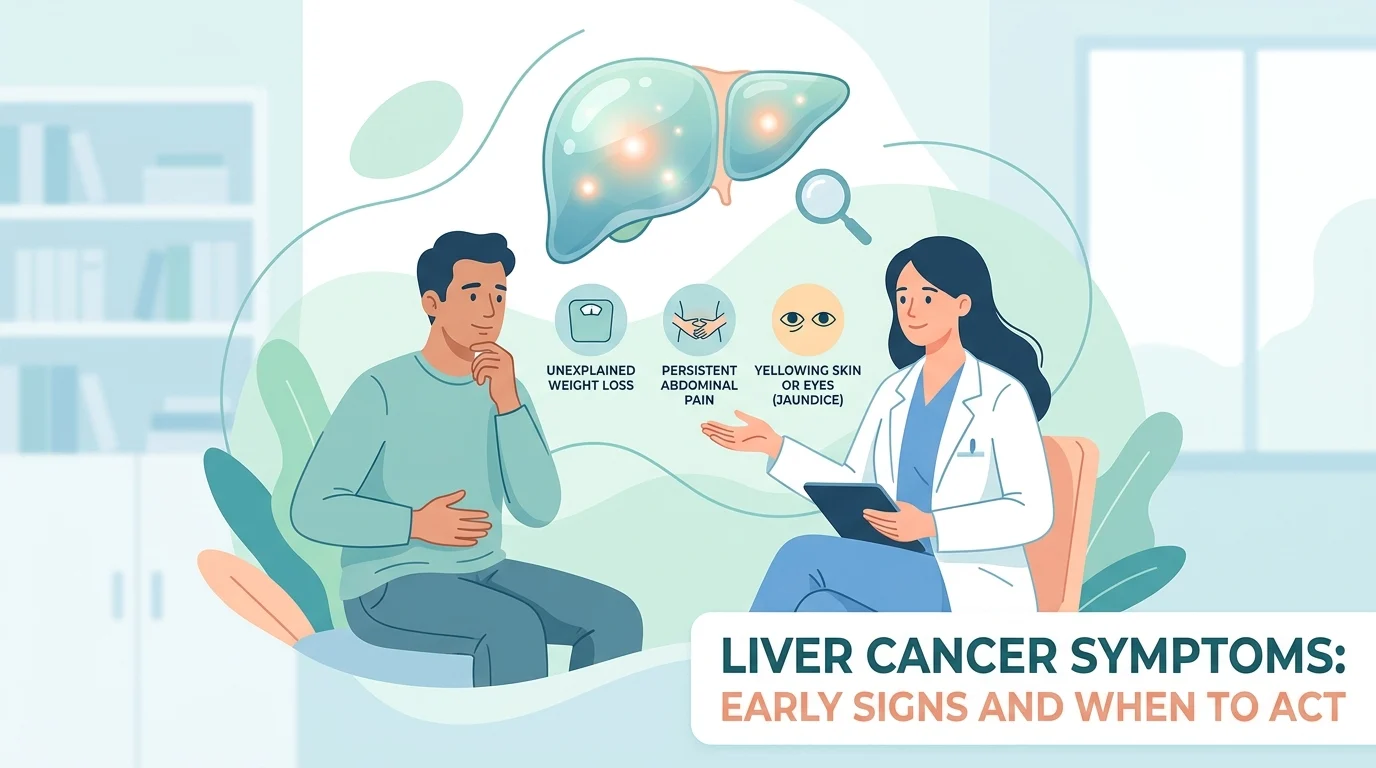
अधिकांश शुरुआती लिवर कैंसर में कोई लक्षण नहीं होते। जब कुछ महसूस होता है, तो वह आमतौर पर अस्पष्ट होता है और किसी और कारण से जोड़ना आसान होता है। नीचे दी गई तालिका में सबसे अधिक बताए जाने वाले संकेत और उनके पीछे का कारण दिया गया है।.
| संकेत | यह क्या दर्शाता है | सामान्य समय |
|---|---|---|
| बिना कोशिश किए वज़न कम होना | ट्यूमर का सामान्य चयापचय प्रभाव (General Metabolic Effect) | अक्सर सबसे पहले ध्यान में आता है, लेकिन यह किसी एक बीमारी का संकेत नहीं |
| भूख न लगना, जल्दी पेट भरा लगना | पेट पर दबाव, या बीमारी का असर | शुरुआती से मध्यम अवस्था |
| दाईं ओर ऊपरी पेट में दर्द | लिवर के चारों ओर की कैप्सूल (Capsule) में खिंचाव | ट्यूमर (Tumor) का एक निश्चित आकार तक पहुँचना ज़रूरी होता है |
| सामान्य कमज़ोरी और थकान | लिवर की कार्यक्षमता में कमी, एनीमिया (Anemia), या ट्यूमर | धीरे-धीरे होता है, अक्सर अन्य कारणों को ज़िम्मेदार माना जाता है |
| मतली और उल्टी | आस-पास के अंगों का अपनी जगह से खिसकना | मध्यवर्ती (Intermediate) |
| दाईं पसलियों के नीचे एक कठोर गाँठ | बढ़ा हुआ लिवर या महसूस होने वाला ट्यूमर | बाद के चरण में, और यह कभी भी शुरुआती लक्षण का भरोसेमंद संकेत नहीं होता |
इस सूची में दिए गए हर लक्षण के कहीं अधिक सामान्य कारण हो सकते हैं। अनजाने में वज़न कम होना और थकान चिकित्सा विज्ञान में सबसे कम विशिष्ट लक्षणों में से हैं। इन्हें महत्त्व देने वाली बात है — संदर्भ: यही लक्षण किसी ऐसे व्यक्ति में जिसे पहले से सिरोसिस (Cirrhosis) या क्रोनिक हेपेटाइटिस बी (Chronic Hepatitis B) हो, उसके लिए कुछ अलग मायने रखता है, बजाय उस व्यक्ति के जिसका लिवर स्वस्थ हो।.
बाद के और उन्नत चरण के लक्षण
जैसे-जैसे बीमारी बढ़ती है, लक्षण अधिक स्पष्ट होते जाते हैं, क्योंकि वे ट्यूमर की बजाय लिवर की कार्यक्षमता में आई कमी को दर्शाते हैं।.
- पीलिया (Jaundice), यानी त्वचा और आँखों के सफ़ेद हिस्से का पीला पड़ना
- गहरे रंग का पेशाब, और हल्के, धूसर या चॉकी-सफ़ेद रंग का मल
- एसाइटिस (Ascites) के कारण पेट में सूजन, जिसमें पेट में तरल पदार्थ जमा हो जाता है
- बिना किसी चकत्ते के त्वचा में खुजली, जो पित्त उत्पादों के जमाव के कारण होती है
- आसानी से नील पड़ना या रक्तस्राव होना, क्योंकि लिवर ही थक्का जमाने वाले कारक (Clotting Factors) बनाता है
- बिना किसी स्पष्ट संक्रमण के बुखार
- भ्रम या नींद आना, जो हेपेटिक एन्सेफैलोपैथी (Hepatic Encephalopathy) के नाम से जाना जाने वाला देर से प्रकट होने वाला लक्षण है
स्टेज 4 (Stage 4) और अंतिम चरण के लक्षण
उन्नत बीमारी में उपरोक्त लक्षणों के साथ-साथ वे लक्षण भी जुड़ जाते हैं जहाँ कैंसर फैल चुका होता है — अक्सर फेफड़ों, हड्डियों या पेट की परत में। हड्डियों में दर्द, साँस लेने में तकलीफ़, पैरों में अत्यधिक सूजन, और मांसपेशियों व वज़न में भारी कमी प्रमुख रूप से सामने आती है। SEER डेटा के अनुसार, 21 प्रतिशत मामलों में निदान के समय कैंसर पहले से ही दूर के अंगों तक फैल चुका होता है, जिसमें पाँच वर्षीय सापेक्ष जीवित रहने की दर केवल 3.6 प्रतिशत है — जबकि लिवर तक सीमित बीमारी में यह दर 37.4 प्रतिशत है। यह अंतर ही इस बात का सबसे बड़ा तर्क है कि लक्षण प्रकट होने से पहले ही बीमारी का पता लगाना क्यों ज़रूरी है।.
क्या महिलाओं में लिवर कैंसर के लक्षण अलग होते हैं?
लक्षण स्वयं एक जैसे ही होते हैं। अंतर इस बात में है कि यह बीमारी किसे होती है: लिवर कैंसर पुरुषों में काफ़ी अधिक पाया जाता है, और पुरुष लिंग एक स्थापित जोखिम कारक है जिसकी पुष्टि बड़े साक्ष्य-आधारित अध्ययनों में हुई है। निदान के समय औसत आयु 68 वर्ष होती है। महिलाओं में कोई अलग लक्षण पैटर्न नहीं होता, और इस विषय पर की जाने वाली खोजें आमतौर पर लक्षणों में नहीं, बल्कि बीमारी की घटना दर में इस अंतर को दर्शाती हैं।.
लिवर कैंसर के कारण और जोखिम में कौन है
लिवर कैंसर (Liver Cancer) लगभग हमेशा क्रोनिक लिवर क्षति (Chronic Liver Injury) की पृष्ठभूमि में विकसित होता है। 2025 में प्रकाशित एक व्यापक समीक्षा (Umbrella Review), जिसमें 175 मेटा-विश्लेषणों (Meta-analyses) को एकत्रित किया गया और 101 संभावित जोखिम कारकों की पहचान की गई, में पाया गया कि क्रोनिक हेपेटाइटिस बी (Chronic Hepatitis B) से जोखिम लगभग 12.5 गुना और क्रोनिक हेपेटाइटिस सी (Chronic Hepatitis C) से लगभग 11.2 गुना बढ़ जाता है। एंटीवायरल उपचार (Antiviral Treatment) और वायरोलॉजिकल रिस्पॉन्स (Virological Response) से यह जोखिम कम हो सकता है।.
- क्रोनिक हेपेटाइटिस बी (Chronic Hepatitis B) या हेपेटाइटिस सी (Hepatitis C) संक्रमण — ये दुनिया भर में सबसे प्रमुख कारण हैं
- किसी भी कारण से होने वाला सिरोसिस (Cirrhosis), जिसमें शराब से संबंधित लिवर रोग (Alcohol-related Liver Disease) भी शामिल है
- मेटाबॉलिक डिसफंक्शन-एसोसिएटेड फैटी लिवर डिजीज (Metabolic Dysfunction-associated Fatty Liver Disease), मोटापा (Obesity) और टाइप 2 डायबिटीज (Type 2 Diabetes)
- अत्यधिक शराब का सेवन और धूम्रपान
- हेरेडिटरी हेमोक्रोमैटोसिस (Hereditary Hemochromatosis) और अन्य वंशानुगत लिवर रोग
- अफ्लाटॉक्सिन (Aflatoxin) का संपर्क — कुछ क्षेत्रों में संग्रहित अनाज और मेवों में फफूंद (Mold) के दूषण से
- पुरुष लिंग और अधिक उम्र
उसी समीक्षा में कम जोखिम से जुड़े कारक भी बताए गए, जैसे कॉफी का सेवन, स्वस्थ आहार, और कुछ सामान्य दवाओं के संकेत। ये अवलोकन संबंधी डेटा (Observational Data) से प्राप्त जनसंख्या-स्तरीय संबंध हैं, न कि कोई निर्देश — इस सूची में कुछ भी देखकर अपने डॉक्टर से बात किए बिना कोई दवा शुरू या बंद न करें।.
लक्षण सही उपकरण क्यों नहीं हैं, और नियमित निगरानी (Surveillance) क्यों जरूरी है
यह सबसे महत्वपूर्ण बात है। चूँकि शुरुआती लिवर कैंसर (Liver Cancer) में कोई लक्षण नहीं होते, इसलिए दिशानिर्देश इसे पहचानने के लिए लक्षणों पर निर्भर नहीं रहते। उच्च जोखिम वाले लोगों के लिए नियमित निगरानी (Surveillance) की सिफारिश की जाती है — आमतौर पर हर छह महीने में पेट का अल्ट्रासाउंड (Abdominal Ultrasound), और सिरोसिस (Cirrhosis) या उच्च जोखिम वाले क्रोनिक हेपेटाइटिस बी (Chronic Hepatitis B) के मरीजों में अल्फा-फेटोप्रोटीन (Alpha-fetoprotein) ब्लड टेस्ट के साथ या उसके बिना। निगरानी से शुरुआती चरण में पहचान, उपचारात्मक इलाज और लिवर कैंसर से होने वाली मृत्यु दर में कमी देखी गई है। यदि आप इनमें से किसी समूह में आते हैं, तो सबसे उपयोगी कदम यह है कि आप यह सुनिश्चित करें कि आप वास्तव में किसी निगरानी कार्यक्रम (Surveillance Program) में नामांकित हैं — न कि केवल लक्षणों की सूची याद करें।.
रक्त परीक्षण (Blood Test) क्या दिखा सकते हैं और क्या नहीं
एक सामान्य लिवर पैनल (Liver Panel) उन एंजाइमों (Enzymes) को मापता है जो लिवर कोशिकाओं के क्षतिग्रस्त होने पर निकलते हैं — यह नहीं बताता कि कोई ट्यूमर (Tumor) मौजूद है या नहीं, और हमारा लिवर फंक्शन टेस्ट (Liver Function Tests) गाइड explains how those markers are read as a pattern. The individual values each carry their own meaning: for the enzyme most often flagged first, open our ALT blood test guide, and for its usual companion, check our AST blood test guide. Jaundice is explained in our total bilirubin guide, and the protein that falls as liver function declines is covered in our low albumin guide.
Alpha-fetoprotein is the blood marker used in surveillance, and it is widely misunderstood. A raised level most often reflects a benign liver condition rather than cancer, and a normal level does not rule cancer out, because a substantial share of liver cancers never produce it; read our AFP blood test guide before drawing conclusions from a single value. Because hepatitis status determines whether surveillance applies at all, testing for it matters: see our hepatitis B surface antigen guide and our hepatitis blood test guide.
डॉक्टर से कब मिलें
Contact a clinician promptly, rather than waiting, in any of these situations.
- Yellowing of the skin or eyes, at any age and with any other symptom
- Pale or chalky stools together with dark urine
- New abdominal swelling, or clothes becoming tight around the waist over weeks
- Unintentional weight loss of more than about 5 percent of body weight within six months
- Persistent upper right abdominal pain lasting more than two weeks
- A hard lump felt below the right rib cage
- Any new or worsening symptom in someone with known cirrhosis, hepatitis B, or hepatitis C
Confusion, drowsiness, vomiting blood, or black tarry stools in someone with liver disease are emergencies and need immediate care rather than an appointment.
Survival rates in context
Liver cancer survival statistics are sobering, and they are also frequently misapplied. The 21.9 percent five-year relative survival covers every stage and every type together, and it describes people diagnosed in past years and treated with the methods available then. Stage changes the picture substantially: 37.4 percent at five years for localized disease, 13.4 percent for regional spread, and 3.6 percent for distant disease. Underlying liver function also shapes the outlook independently of the tumor, because treatment options depend on how much healthy liver remains. No statistic predicts an individual outcome, and the figures cannot account for a specific person’s treatment plan or response.
नवीनतम वैज्ञानिक प्रगति
Research over the past three years has concentrated on the problem this article opened with: finding liver cancer before symptoms appear. The findings below come from peer-reviewed studies and guidelines, and none of them changes what any individual should do without a clinician’s input.
The limits of current surveillance are now well documented. A 2024 review of surveillance strategies concluded that ultrasound alone has suboptimal sensitivity for early-stage disease, particularly in people with obesity and in non-viral liver disease, and that adding alpha-fetoprotein improves detection but still misses more than a third of early-stage cancers. That acknowledged gap is what the rest of this work is trying to close.
Blood-based biomarker panels are the most advanced response. The best-studied is the GALAD score, which combines sex, age, alpha-fetoprotein, AFP-L3, and des-gamma-carboxy prothrombin into a single value. A phase 3 validation study published in 2024 followed 1,558 patients with cirrhosis across seven centers for a median of 2.2 years, during which 109 developed liver cancer. Measured in blood drawn up to 12 months before diagnosis, GALAD achieved an area under the curve of 0.78 against 0.66 for alpha-fetoprotein alone, and at matched specificity of 82 percent its sensitivity was 62 percent against 41 percent. In plain terms, the panel found meaningfully more cancers a year earlier than the single marker, while still missing a substantial share. A 2025 systematic review of 44 studies and 33,100 patients pooled the three commercially available panels and found early-stage sensitivities of 70.1 to 74.1 percent with specificities of 83.3 to 87.2 percent, with no significant difference between them and high statistical heterogeneity across studies.
The decisive evidence is not yet in. A phase 4 randomized trial began enrolling in 2024 across 15 United States sites, comparing semi-annual ultrasound with or without alpha-fetoprotein against semi-annual GALAD in 5,500 patients with cirrhosis or chronic hepatitis B, with reduction in late-stage cancer as the primary endpoint measured at five and a half years. A separate real-world implementation study of a related panel is running in the United Kingdom through 2030. A search of ClinicalTrials.gov in September 2026 returns 42 recruiting studies in liver cancer screening and surveillance. Until those trials report, ultrasound with or without alpha-fetoprotein remains the recommended standard, and a biomarker panel is an adjunct discussed with a specialist rather than a replacement.
Guidelines have moved in parallel. The European Association for the Study of the Liver published updated clinical practice guidelines on managing hepatocellular carcinoma in 2024, introducing personalized surveillance based on individual risk assessment, standardized imaging criteria, and clearer transitions between surgical, locoregional, and systemic therapies. On the treatment side, a network meta-analysis of 25 studies and 4,548 patients with early-stage disease found surgical resection associated with better disease-free survival at one and three years than radiofrequency or microwave ablation, though the comparison varied by region and the studies were mostly observational. Which option suits a given patient depends on tumor size and number, liver function, and overall health, and remains a multidisciplinary decision.
शब्दकोष
| अवधि | अर्थ |
|---|---|
| Hepatocellular carcinoma | The most common primary liver cancer, about 90 percent of cases. |
| सिरोसिस (Cirrhosis) | Permanent scarring of the liver, the main setting in which liver cancer arises. |
| निगरानी (Surveillance) | Planned repeat testing in people at high risk, to find cancer before symptoms. |
| Alpha-fetoprotein | A protein used as a blood marker in liver cancer surveillance. |
| GALAD score | A panel combining sex, age and three blood markers into one detection score. |
| Ascites | Fluid collecting in the abdomen, causing swelling. |
| पीलिया | Yellowing of skin and eyes from a build-up of bilirubin. |
| Ablation | Destroying a small tumor with heat, cold, or alcohol through a needle. |
| Relative survival | Survival compared with people of the same age without the cancer. |
अक्सर पूछे जाने वाले प्रश्नों
What is the first sign of liver cancer?
There often is none. When something is noticed first, it is usually unintentional weight loss, loss of appetite, or vague discomfort in the upper right abdomen, all of which have far more common causes. Jaundice and abdominal swelling are later signs, not first ones. This is precisely why people at high risk are offered scheduled scans rather than being told to watch for symptoms.
Can liver cancer show up in a routine blood test?
Not reliably. A liver panel can be entirely normal in someone with liver cancer, and it can be abnormal for dozens of reasons that have nothing to do with cancer. Alpha-fetoprotein is more specific but still misses a large share of cases and rises in benign liver conditions. Imaging, usually ultrasound followed by a CT or MRI scan, is what identifies a tumor.
Where do you feel liver cancer pain?
Typically in the upper right part of the abdomen, just below the ribs, sometimes radiating to the right shoulder blade. The pain comes from stretching of the capsule around the liver rather than from the liver tissue itself, which has no pain nerves, so it appears only once a tumor has reached a certain size.
How quickly does liver cancer progress?
It varies widely. Some hepatocellular carcinomas double in size over several months, others much faster, and progression also depends on the state of the underlying liver. The six-month interval used in surveillance programs reflects this typical pace rather than an arbitrary schedule.
Can liver cancer be cured?
Yes, when it is found early. Surgical removal, liver transplant, and ablation can be curative for small tumors in a liver that still functions well, and five-year relative survival for localized disease is 37.4 percent. Once the cancer has spread beyond the liver, treatment aims to control the disease and maintain quality of life rather than to cure.
Who should be screened for liver cancer?
Guidelines recommend surveillance for adults with cirrhosis from any cause and for selected people with chronic hepatitis B, usually an ultrasound every six months with or without an alpha-fetoprotein test. If you have either condition, ask your clinician directly whether you are enrolled, because participation rates remain low even among people who qualify.
सूत्रों का कहना है
- Cancer Stat Facts: Liver and Intrahepatic Bile Duct Cancer — SEER Program, National Cancer Institute
- Liver Cancer Treatment (PDQ) Patient Version — National Cancer Institute, National Institutes of Health
- Liver Cancer — MedlinePlus, National Library of Medicine
- Liver Cancer, Symptoms and Causes — Mayo Clinic
- Liver Cancer: Symptoms, Signs, Causes and Treatment — Cleveland Clinic
- EASL Clinical Practice Guidelines on the management of hepatocellular carcinoma — Journal of Hepatology, 2024 (indexed in PubMed)
- Wang J. et al. Risk factors for hepatocellular carcinoma: an umbrella review of systematic review and meta-analysis — Annals of Medicine, 2025 (indexed in PubMed)
- Min Y. et al. Ablative Treatments and Surgery for Early-Stage Hepatocellular Carcinoma: A Network Meta-Analysis — Journal of Surgical Research, 2024 (indexed in PubMed)
- Singal A.G. et al. Advancing Surveillance Strategies for Hepatocellular Carcinoma: A New Era of Efficacy and Precision — Journal of Clinical and Experimental Hepatology, 2024
- Marsh T.L. et al. A Phase 3 Biomarker Validation of GALAD for the Detection of Hepatocellular Carcinoma in Cirrhosis — Gastroenterology, 2024
- Jarrah M. et al. Performance of GALAD, GAAD, and ASAP for Early HCC Detection in Chronic Liver Disease: A Systematic Review and Meta-Analysis — Liver Cancer, 2025
- Singal A. et al. National Liver Cancer Screening Trial (TRACER) study protocol — Hepatology Communications, 2024
- National Liver Cancer Screening Trial, TRACER (NCT06084234) — ClinicalTrials.gov
- Real-world GAAD Algorithm Implementation and Validation to Improve Surveillance and Early Detection of Hepatocellular Carcinoma (NCT05971108) — ClinicalTrials.gov
अन्य लेख
- AFP रक्त परीक्षण: अपने परिणाम कैसे समझें
- लिवर फंक्शन टेस्ट (एलएफटी): अपने लिवर पैनल को कैसे पढ़ें
- SGPT ब्लड टेस्ट: सामान्य सीमा, उच्च स्तर और कारण
- AST ब्लड टेस्ट: आपके लिवर एंज़ाइम स्तर का क्या अर्थ है
- कुल बिलीरुबिन स्तर: सामान्य सीमा, कारण और देखभाल
- एल्ब्यूमिन का निम्न स्तर: कारण, लक्षण और जोखिम
- HBsAg पॉजिटिव: इसका क्या मतलब है और आगे क्या होता है
- हेपेटाइटिस ब्लड टेस्ट: आपके परिणामों का क्या मतलब है
Liver results are much easier to act on when each enzyme, protein, and marker is explained next to the others rather than read alone. AI DiagMe की मदद से अपने लैब परिणामों को समझें, जो आपकी रिपोर्ट को लाइन दर लाइन पढ़ता है और प्रत्येक मान को सरल भाषा में समझाता है, जिसकी व्याख्या चिकित्सकों की एक समिति द्वारा समीक्षित होती है।



