




The words benign and malignant do a great deal of work in a very short sentence, and most people meet them at the worst possible moment: on a report, without context, usually the day before they can speak to anyone about it. The distinction itself is not complicated. What causes most of the confusion is something else entirely, which is that the two words describe a biological behavior, while the tests people usually have in hand at that point, a scan and a blood panel, can only estimate the probability of that behavior. This guide explains what actually separates the two, what sits between them, how the call is genuinely made, and why the third answer, indeterminate, is far more common than anyone expects.
The core difference is invasion
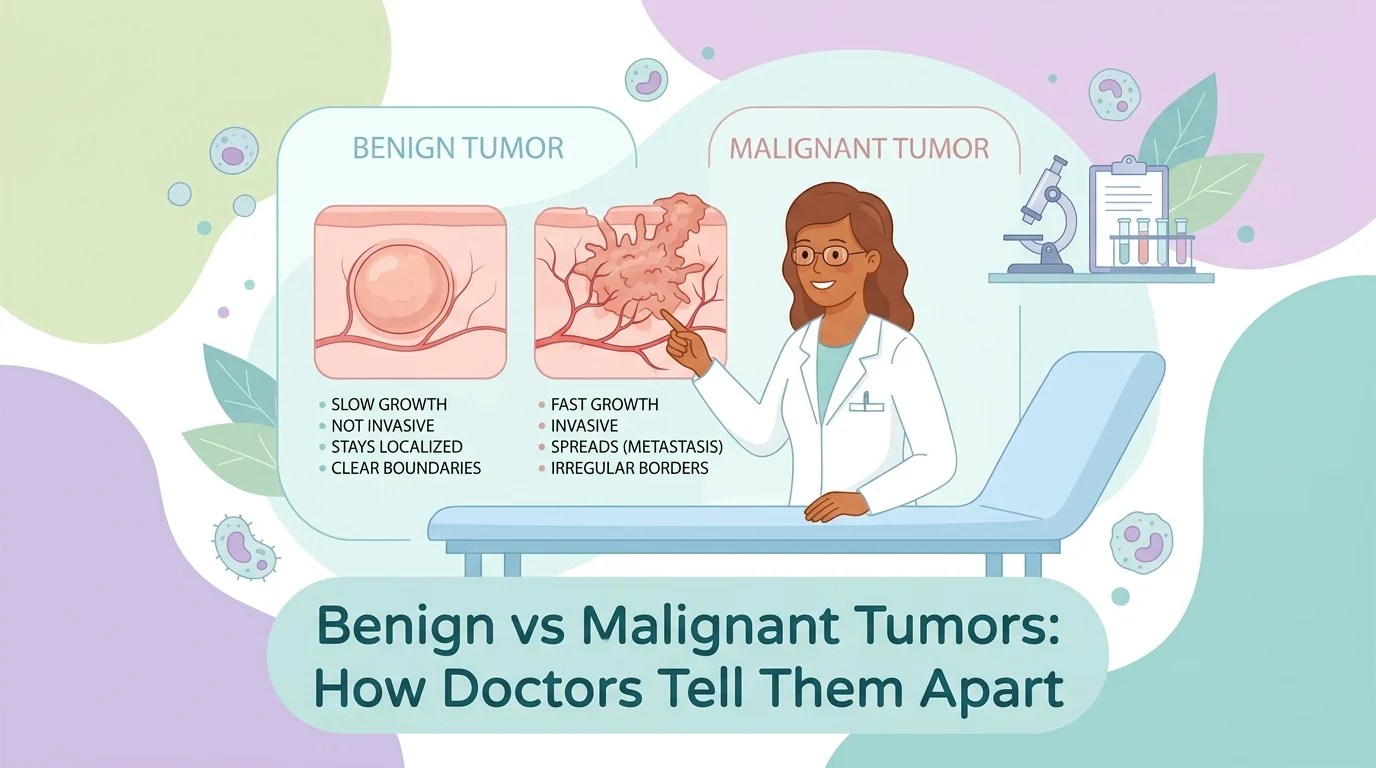
Strip away everything else and one property separates benign from malignant: whether the cells invade.
A benign tumor grows where it started. It can become large, it can press on neighboring structures, and it can cause real harm by doing so, but it stays a single mass with a boundary. Removed completely, it usually does not come back.
A malignant tumor grows into surrounding tissue rather than pushing it aside, and cells can break away, travel through blood or lymph, and establish new tumors elsewhere. That capacity to invade and to spread is what the word cancer describes. As the National Cancer Institute puts it, cancer cells grow in the absence of signals telling them to grow, ignore the signals that normally tell cells to stop dividing or to die, and invade nearby areas and spread to other parts of the body.
Everything else people list as a difference, such as growth speed, shape, or appearance under a microscope, is a clue pointing toward or away from that one property. None of it is the definition.
Benign and malignant compared
| Feature | Benign | Malignant |
|---|---|---|
| Invades nearby tissue | No, it pushes tissue aside | Yes, it grows into it |
| Spreads to distant organs | No | Can do, through blood or lymph |
| Border | Usually well defined, often encapsulated | Often irregular or poorly defined |
| Cell appearance | Close to the normal tissue it came from | Increasingly abnormal and disorganized |
| Growth | Usually slow, sometimes stable for years | Variable, often faster |
| Recurrence after complete removal | Uncommon | Possible, which is why follow-up continues |
| Can still be dangerous | Yes, by pressing on vital structures | Yes, by invading and spreading |
That last row matters more than its position suggests. A benign meningioma pressing on the brain, or a benign tumor obstructing an airway or a bile duct, is a serious medical problem. Benign means not cancer. It does not mean harmless.
The grey zone in between
Tissue does not jump from normal to cancerous. There is a recognized sequence of changes in between, and the terms for them appear on reports often enough to be worth knowing.
| Term | What it describes | Is it cancer? |
|---|---|---|
| Hyperplasia | Cells multiplying faster than normal but still looking normal | No |
| Dysplasia | Cells looking abnormal and tissue losing its organization | No, but it is watched |
| Carcinoma in situ | Abnormal cells that have not broken through into nearby tissue | Called stage 0; not invasive |
Most hyperplasia and mild dysplasia never progress. The reason these findings are reported and followed at all is that the sequence sometimes does move forward, and it is far easier to act before invasion than after. This is also why certain benign growths are removed on sight: some colon polyps, for example, are taken out during colonoscopy precisely because a minority of them would eventually become malignant.
What malignant means on a report, and what grade adds
If a report says malignant, it means a pathologist looked at the cells and concluded they have the features of invasive cancer. Two further words usually appear alongside it, and they are commonly confused with each other.
Grade describes how abnormal the cells look. Well-differentiated cells still resemble the tissue they came from and are graded low; undifferentiated cells have lost that resemblance and are graded high. The usual scale runs from grade 1, well differentiated, to grade 4, undifferentiated. Stage is a different measurement entirely: it describes how large the tumor is and how far it has spread. Grade is about appearance and likely aggressiveness, stage is about extent. A tumor can be high grade and early stage, or the reverse.
How the call is actually made
What imaging can and cannot do
A scan describes shape, size, density, borders, and behavior with contrast. From those features a radiologist estimates the probability of malignancy, often expressed through a structured reporting category rather than a plain word. That estimate is genuinely useful, and it is not a diagnosis. Features that usually indicate a benign lesion appear in some cancers, and features that look alarming turn out to be benign often enough that operating on imaging alone is now considered a cause of overtreatment rather than a form of caution.
Why tumor markers cannot make this call
This deserves stating plainly, because it is the single most common misunderstanding among people reading their own results. No blood tumor marker distinguishes a benign tumor from a malignant one. Markers are proteins that healthy tissue also produces, and they rise in inflammation, infection, benign growths, pregnancy, smoking, and several ordinary conditions. Our PSA blood test guide explains why a raised value most often reflects a benign prostate; our CA 125 blood test guide covers a marker that rises with endometriosis and menstruation; and our CEA blood test guide describes a marker that smoking alone will elevate. Markers are used to monitor a cancer already diagnosed, and sometimes to support an assessment. They do not decide the question in this article.
Biopsy, and why a benign result is weaker than a malignant one
The decision belongs to tissue. A needle or surgical sample goes to a pathologist, who examines the cells and, increasingly, tests them for specific molecular changes. That is the reference standard everything else is measured against.
One feature of biopsy is worth understanding because it explains a lot of clinical behavior that otherwise seems overcautious. The evidence a biopsy provides is asymmetric. When a sample shows cancer, it is cancer; false positives are rare. When a sample shows no cancer, it may mean the lesion is benign, or it may mean the needle missed. That is why a benign biopsy of a suspicious lesion is often followed by repeat imaging rather than discharge, and why a doctor may still recommend removal after a reassuring sample.
The third answer: indeterminate
People expect a binary and are unprepared for the most common real-world outcome in difficult cases, which is that the result sits between the two. Structured reporting systems across specialties all reserve categories for exactly this. A thyroid biopsy can return cells that are adequate to read but cannot be called benign or malignant; our thyroid nodule blood test guide walks through those categories. Lung screening programs define a formal indeterminate result alongside positive and negative. Kidney imaging regularly produces masses that cannot be classified, and a meaningful proportion of them are benign, as our kidney cancer guide explains.
Indeterminate is not a failure of the test or of the person reading it. It is an honest statement that the available information does not settle the question, and it has its own management: repeat imaging at an interval to look for growth, molecular testing of the sample, a different imaging method, or a further biopsy. Being told a result is indeterminate is frustrating, but it is far better than a confident answer that turns out to be wrong in either direction.
Common benign tumors people worry about
Benign tumors are extremely common, and most people carry at least one without knowing. Lipomas, which are soft fatty lumps under the skin, are the most frequent. Others include adenomas in glandular tissue, fibroids in the uterus, hemangiomas made of blood vessels, meningiomas around the brain and spinal cord, osteomas in bone, and a long list of skin growths such as seborrheic keratoses, skin tags, and cherry angiomas. Thyroid nodules, kidney cysts, and liver hemangiomas are found so often on scans done for other reasons that they are frequently treated as background findings rather than problems.
When a benign finding still needs treatment
- It presses on something important, such as the brain, spinal cord, an airway, a nerve, or a blood vessel
- It blocks a passage, for example a bile duct or the bowel
- It produces hormones, which some benign endocrine tumors do
- It bleeds, causes pain, or keeps growing
- It belongs to a type with a recognized risk of becoming malignant, such as certain colon polyps
- It cannot be confidently distinguished from a malignant lesion, and monitoring is not appropriate
Latest scientific advances
Research over the past three years has focused almost entirely on the grey zone, which is the part of this subject where better tools would actually change what happens to people. The findings below come from peer-reviewed studies and guidelines, simplified for general readers, and none of them changes what any individual should do without a clinician’s input.
A systematic review published in 2024 quantified the asymmetry of biopsy evidence described above. Across 81 studies of image-guided biopsy of lung lesions, specificity and positive predictive value were 1.00 in almost all studies, meaning a positive result was essentially always correct, while sensitivity ranged from 0.35 to 0.97 depending on the technique, meaning negative results were far less dependable. Median accuracy was highest for CT-guided biopsy at 0.91, which also carried the highest complication rate at 30 percent, against 3 percent for the bronchoscopic ultrasound approach. The authors also argued that indeterminate results should be counted as false negatives when accuracy is calculated, on the principle that the point of the test is to reach a diagnosis.
Lung screening has formalized the indeterminate category rather than trying to eliminate it. A 2025 nodule management recommendation from the European Society of Thoracic Imaging defines positive, indeterminate, and negative screen results explicitly, uses volume measurement software to track growth as the primary way of assessing solid nodules, and states its aims as reducing the number of follow-up examinations while avoiding both missed progression and overtreatment. Treating uncertainty as a managed category, rather than a problem to resolve immediately, is the direction of travel across specialties.
Molecular and imaging tools are being developed specifically to separate benign from malignant without surgery. A 2025 joint procedure standard from the nuclear medicine societies set out an approach to indeterminate kidney masses using two complementary agents: one antibody-based tracer that binds a protein found on clear cell kidney cancer but generally not on other renal tumors, and one mitochondrial tracer that accumulates in benign or indolent lesions such as oncocytomas and not in clear cell cancer. Used together, a positive result on one and a negative on the other point in opposite directions, which is more informative than either alone. Separately, a 2025 meta-analysis of four studies and 534 participants found that measuring methylation of two genes in pleural fluid distinguished malignant from benign effusions with a pooled sensitivity of 85 percent and specificity of 92 percent, outperforming cytology, though the small number of studies means this remains promising rather than established.
Artificial intelligence is being tested on the same problem, with results that are encouraging and not yet decisive. A 2024 systematic review and meta-analysis of 51 studies applying machine learning to brain tumor imaging reported a pooled sensitivity of 0.90 and specificity of 0.93 for distinguishing benign from malignant tumors. A 2025 systematic review examined artificial intelligence applied to digitized slides in thyroid biopsies that had been called indeterminate, across 13 studies covering 494 such cases, and found the approach promising for reducing subjective variation between readers, while identifying the absence of standardization as the main obstacle to clinical use. Both are retrospective bodies of work: the tools are positioned as support for the pathologist or radiologist rather than as a replacement, and prospective validation is what is missing.
Glossary
| Term | Meaning |
|---|---|
| Tumor | Any abnormal mass of cells, benign or malignant. |
| Neoplasm | The medical term for a tumor; means new growth. |
| Lesion | A deliberately neutral word for any area of abnormal tissue. |
| Metastasis | A tumor formed by cells that traveled from the original cancer. |
| Grade | How abnormal the cells look, from well to poorly differentiated. |
| Stage | How large the tumor is and how far it has spread. |
| Dysplasia | Abnormal-looking cells that have not become cancer. |
| Carcinoma in situ | Abnormal cells confined to where they started, called stage 0. |
| Indeterminate | A result that cannot be classified as benign or malignant. |
Frequently asked questions
What does malignant mean?
Malignant means the cells are capable of invading nearby tissue and of spreading to other parts of the body. It is the property that defines cancer. Benign means the growth stays where it started and cannot spread, although it can still cause harm by pressing on something important.
Can a benign tumor turn into a malignant one?
Most do not, and the great majority of benign tumors remain benign for life. Some categories carry a recognized risk of transformation, which is why certain colon polyps are removed when found and why some lesions are monitored rather than ignored. If a doctor recommends removing or watching something benign, that recognized risk is usually the reason.
Can a scan tell whether a tumor is benign or malignant?
Not definitively. Imaging estimates probability from size, shape, borders, and behavior with contrast, and it does this well enough to guide what happens next. Benign lesions can look worrying and cancers can look reassuring. Tissue examined by a pathologist is what settles the question.
Can a blood test tell benign from malignant?
No. Tumor markers rise in many benign conditions and are normal in a substantial share of cancers, so they cannot make this distinction. They are used mainly to monitor a cancer that has already been diagnosed, and sometimes to add context to an assessment.
My result says indeterminate. What happens now?
It means the information available does not settle the question, which is common and is not a mistake. The usual next steps are repeat imaging after an interval to see whether anything has changed, molecular testing of the existing sample, a different type of scan, or a further biopsy. Which of these applies depends on the organ and on how suspicious the finding was.
Is a benign tumor dangerous?
It can be, which is why benign is not the same as harmless. A benign tumor pressing on the brain, blocking an airway or a bile duct, bleeding, or producing hormones needs treatment. What benign does mean is that it will not invade surrounding tissue or spread elsewhere.
What is the difference between grade and stage?
Grade describes how abnormal the cells look under the microscope, from well differentiated at grade 1 to undifferentiated at grade 4. Stage describes how big the tumor is and how far it has spread. They are independent, and a tumor can be high grade but caught early.
Sources
- What Is Cancer? — National Cancer Institute, National Institutes of Health
- Tumor Grade — National Cancer Institute, National Institutes of Health
- Benign Tumors — MedlinePlus, National Library of Medicine
- Benign Tumor: Definition, Types and Symptoms — Cleveland Clinic
- Magnini A. et al. Diagnostic accuracy of imaging-guided biopsy of peripheral pulmonary lesions: a systematic review — Acta Radiologica, 2024 (indexed in PubMed)
- Snoeckx A. et al. Lung cancer screening with low-dose CT: definition of positive, indeterminate, and negative screen results — European Radiology, 2025 (indexed in PubMed)
- Rowe S.P. et al. SNMMI/EANM/ACNM Procedure Standard on the Use of Molecular Imaging for Renal Mass Characterization — Journal of Nuclear Medicine, 2025 (indexed in PubMed)
- Aissani M.S. et al. Diagnostic performance of SHOX2 and RASSF1A gene methylation assays in malignant pleural effusion: a systematic review and meta-analysis — Cancer Cytopathology, 2025 (indexed in PubMed)
- Silva Santana L. et al. Application of Machine Learning for Classification of Brain Tumors: A Systematic Review and Meta-Analysis — World Neurosurgery, 2024 (indexed in PubMed)
- Poursina O. et al. Artificial Intelligence and Whole Slide Imaging Assist in Thyroid Indeterminate Cytology: A Systematic Review — Acta Cytologica, 2025 (indexed in PubMed)
Other articles
- Thyroid Nodule Blood Test: What TSH Really Decides
- Kidney Cancer: Symptoms, Causes, Tests, and Survival
- Thyroid Cancer: Symptoms, Types, Tests, and Survival
- Prostate Cancer: Symptoms, Diagnosis, and Treatment
- Liver Cancer Symptoms: Early Signs and When to Act
- PSA blood test: what your result means and what it doesn’t
- CA 125 blood test: what high and normal results mean
- CEA Blood Test: How to Read Your Results
Most people meet the words benign and malignant on a document they were handed without explanation, next to values and categories nobody walked them through. Understand your lab results with AI DiagMe, which reads your report line by line and explains each value in plain language, with interpretation reviewed by a committee of physicians.